Business Name: BeeHive Homes of Albuquerque West
Address: 6000 Whiteman Dr NW, Albuquerque, NM 87120
Phone: (505) 302-1919
BeeHive Homes of Albuquerque West
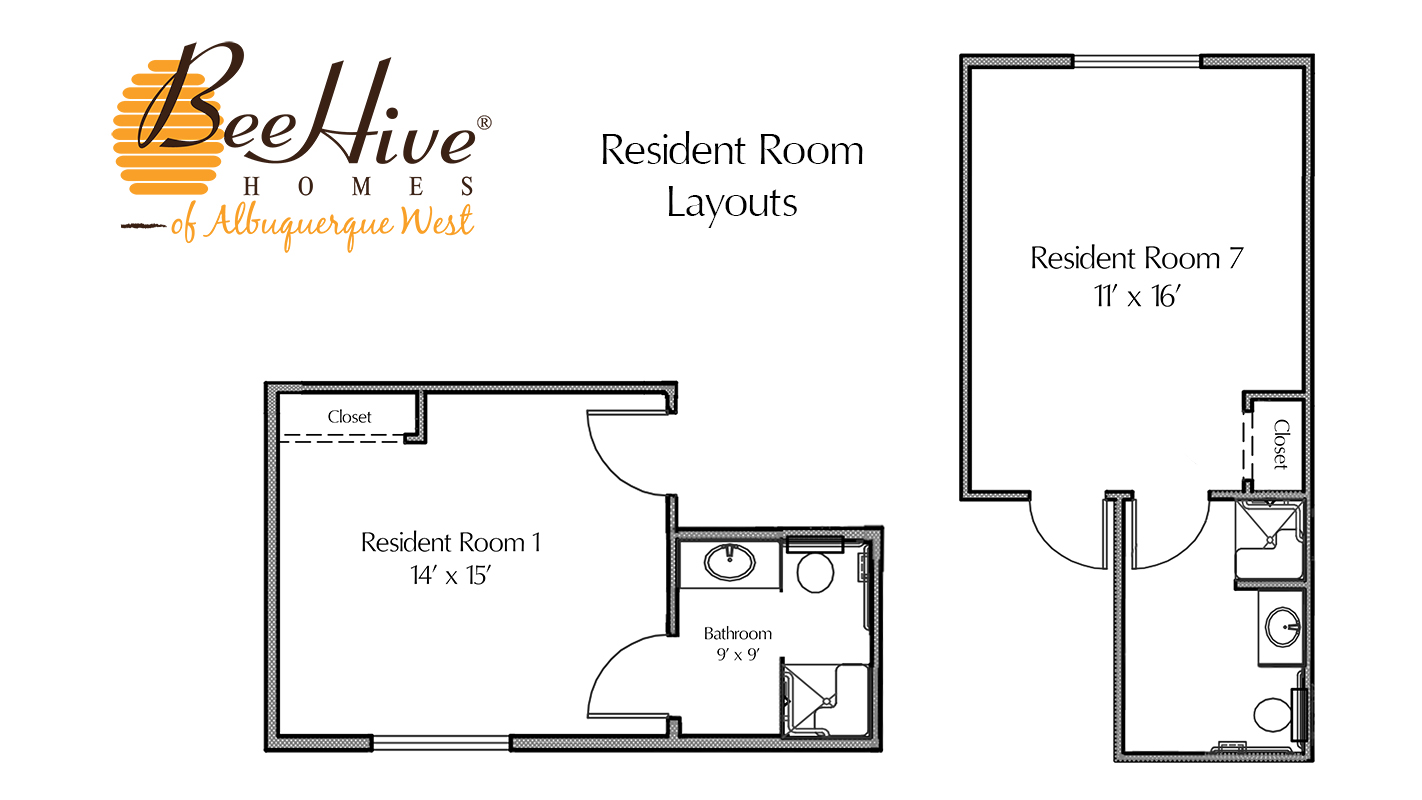
At BeeHive Homes of Albuquerque West, New Mexico, we provide exceptional assisted living in a warm, home-like environment. Residents enjoy private, spacious rooms with ADA-approved bathrooms, delicious home-cooked meals served three times daily, and the benefits of a small, close-knit community. Our compassionate staff offers personalized care and assistance with daily activities, always prioritizing dignity and well-being. With engaging activities that promote health and happiness, BeeHive Homes creates a place where residents truly feel at home. Schedule a tour today and experience the difference.
6000 Whiteman Dr NW, Albuquerque, NM 87120
Business Hours
Monday thru Saturday: 10:00am to 7:00pm
Facebook: https://www.facebook.com/BeehiveABQW/
Choosing an assisted living community is seldom just a real estate decision. For most households, it is a turning point in a loved one's life, specifically around the most individual routines: getting dressed, bathing, handling medications, and simply getting from bed to chair without a fall. Those Activities of Daily Living, or ADLs, are precisely where small, intimate assisted living settings often outshine large, campus-style communities.
I have actually visited, assessed, and assisted place elders in both kinds of settings throughout the years. The pattern corresponds. Large buildings offer attractive features and busy calendars. Small homes tend to provide more trustworthy, more individualized aid with the fundamentals that really keep someone safe and dignified. The differences are subtle on a sales brochure, and striking in real life.
This short article looks closely at why that takes place, how to decide what your loved one really requires, and where large neighborhoods still have an edge. The objective is not to state a universal winner, however to match environment to individual, particularly around ADLs and hands-on elderly care.
What ADLs Truly Mean in Daily Life
Professionals utilize "ADLs" continuously, so households in some cases nod along without completely envisioning what is consisted of. For positioning decisions, it is worth slowing down and translating jargon into lived moments.
ADLs normally consist of bathing or bathing, dressing, grooming, toileting, transferring (for example, bed to chair), and eating. Sometimes strolling or utilizing a mobility gadget is contributed to the list. On paper, it sounds like a checklist. In real life, each ADL has layers.
Bathing is not just stepping into a shower. It is getting someone to agree to bathe, changing water temperature, supporting a weak knee, washing hair thoroughly, and making certain they are completely dried to avoid skin breakdown. If your mother has dementia and dislikes water on her face, a hurried bath can feel like an attack. A calm, familiar caretaker who understands how to talk her through it can turn a feared experience into a tolerable routine.
Dressing can be the trigger for agitation if someone is pressed to rush, or it can be an opportunity for conversation and orientation. Transferring securely requires both enough staff and the ideal strategy, or the threat of falls increases quickly. Toileting aid is deeply intimate and highly connected to self-respect. Small breakdowns in any of these areas tend to snowball: skipped baths, poor respite care beehivehomes.com hygiene, and an increased danger of urinary system infections, falls, and hospitalizations.
Because ADLs are so relational, the staff-to-resident ratio, the speed of the environment, and the consistency of caretakers matter as much as any official care strategy. This is where size enters into play.
How Size Shapes Care: The Structural Differences
When families compare neighborhoods, they often look first at cost, location, and appearance. Size prowls in the background till you link it to what the day really appears like for a resident.
Large assisted living neighborhoods normally have dozens, sometimes hundreds, of citizens. Wings or floorings might be divided by level of care, memory care, or independent living. The building often seems like a hotel, with a front desk, business cooking area, and formal dining-room. Staffing is scheduled in blocks: day shift, evening, overnight. Ratios can differ extensively, however lots of large residential or commercial properties hover around one direct care employee for 8 to 15 citizens during the day, with fewer at night.
Smaller settings can mean different models. Some are "residential care homes" or "board and care" homes, frequently in a transformed home with 6 to 12 locals. Others are small lodges or homes with 10 to 20 residents organized together. Staffing is usually more versatile and less layered. You might see one caretaker for 3 to 6 locals throughout the day, plus a med tech or nurse who also understands each resident personally.
From the outside, a big structure may feel more remarkable. Inside, size quickly affects 3 things: the time a caretaker can invest with each person, how well personnel know private histories and habits, and how rapidly someone reacts when a resident requirements assist with an ADL. For senior citizens who still manage practically whatever by themselves, the difference might feel small. For those requiring hands-on assisted living support numerous times a day, it ends up being central.
Why Intimate Settings Tend to Support ADLs Better
Over time, I have actually seen small neighborhoods outperform larger ones on ADL results for three main reasons: connection of relationships, slower rate, and fewer handoffs.
In a small home, the personnel typically know each resident's early morning rhythm. They remember that Mr. Carter needs 10 minutes to "heat up" before he can pivot securely out of bed, or that Mrs. Lee chooses to shower every other night after her preferred program. That understanding is not simply written in a chart. It resides in the personnel because they carry out the exact same ADLs with the same individuals day after day.
In large buildings, staffing rosters often alter more frequently. A resident might see 3 different care assistants within two days, particularly across shift modifications. Each aide implies well, however they might not know that your father tends to get orthostatic lightheadedness when he stands too quick, or that your mother needs a calm, repeated hint to sit totally back before a transfer. That lack of familiarity appears in rushed showers, half-finished grooming, and a tendency to back off when a resident withstands, merely because the caretaker can not invest the extra 15 minutes it would require to develop trust.
The physical layout matters too. In a 120-bed neighborhood, a caregiver might be responsible for 2 hallways and spend half their time strolling from room to space. If your parent rings for help getting to the toilet, staff may be six rooms away handling another resident's fall. Even a five to 10 minute hold-up can be the distinction between safe toileting and an incontinent episode that weakens dignity and increases skin risk.
In a 10-resident home, caretakers are rarely more than a couple of steps away. They can hear someone moving toward the restroom, or notification that Mr. Johnson did not come out for breakfast and go check. Lots of ADLs are resolved preemptively, since personnel see and respond to subtle changes before they end up being crises.
A Day in the Life: Large vs. Small, Through ADL Lenses
Imagining a day can clarify the trade-offs better than any abstract chart.
Picture a big assisted living neighborhood. Breakfast is served from 7:30 to 9:00 in the primary dining-room. Transit time from a resident space might be a long corridor plus an elevator ride. One caretaker on the wing has eight homeowners needing some level of assistance up and down. The early morning quickly becomes a rush. Residents who walk independently go initially. Those who need assistance dressing and transferring might not reach the dining-room until 8:45 or later on. Staff do their best, but a resident who is slow or resistant may have their bath "pushed" to the afternoon, then to another day.
Now image a small residential care home with 8 homeowners. Morning is still a hectic time, but the environment is quieter and more versatile. Breakfast is frequently served at a family-style table near the bedrooms, and caregivers can serve citizens in pajamas if required, then help them gown later. The personnel are rarely more than a space away when a resident calls. ADL support becomes a series of small, constant interactions instead of a scramble to hit scheduled tasks.
I have seen citizens who were labeled "resistant to care" in large settings move into small homes and accept bathing and dressing assist with minimal demonstration. The behavior did not alter since of a habits strategy in some abstract sense. It changed since personnel had time to method gradually, usage familiar language, change routines, and develop trust.
Staff Ratios, Training, and Real-World Care
Families often ask for staff ratios as if a number alone will inform the story. Numbers matter a good deal, however context determines what they actually mean.
In a small home with 6 residents and 2 caregivers on daytime shift, each caregiver has time to totally help 3 individuals with early morning ADLs, help with meal preparation, and still react to unscheduled requirements. If one resident has a particularly tough early morning, the other caregiver can cover. Locals see the very same familiar faces, which supports those with dementia or anxiety.
In a big building with 60 citizens on a flooring and 4 caretakers, the ratio on paper may appear comparable, but the work is more segmented. Someone might handle all showers, another might pass medications, another might be accountable for 2 hallways of call lights and basic ADLs. Training can be standardized and often more extensive, which is a real benefit. Nevertheless, when the environment is hectic and task-driven, personnel might default to "get it done" rather of "do it in the way best suited to this person."
From a senior care viewpoint, training and supervision often look better on paper in big communities. There is generally a nurse on site, formal in-service training, and business policies. Small homes differ commonly. Some are outstanding, with knowledgeable caretakers and strong nurse oversight. Others might be thin on official training, relying more on long-time personnel who "just know" how to look after residents.
For hands-on ADLs, however, the simple concern is: does my loved one get the time, repeating, and consistency needed to keep doing as much as possible for themselves, with support where needed? Intimate settings tend to win on that, especially for elders who have a mix of physical and cognitive needs.
When a Big Neighborhood Might Be the Better Fit
It would be misleading to state small is constantly much better for every older grownup. There are specific situations where a bigger assisted living neighborhood has clear benefits, even for citizens with ADL needs.
Some seniors really prosper on range, social energy, and structured activities. A retired instructor or executive who still delights in lectures, trips, and numerous clubs might feel confined in a small home with just a couple of fellow citizens. Even if they need assistance bathing and dressing, the overall quality of life may be greater in a large, active setting.
Medical complexity is another element. While assisted living is not the like experienced nursing, bigger communities more frequently have 24/7 nurse existence, on-site rehabilitation, or close relationships with checking out physicians and therapists. For a resident with frequent medication modifications, breakable diabetes, or a new stroke, that clinical infrastructure can be valuable. In those cases, you may accept some compromises on one-to-one ADL time in exchange for much better tracking and rapid response.
Cost and availability likewise matter. In some regions, there are even more large neighborhoods than small homes, or the small homes have restricted openings. Families sometimes utilize large neighborhoods as a kind of respite care, giving a short-term break to caregivers while a loved one recovers from a disease or while everybody assesses longer-term choices. For a planned brief stay, the richness of amenities in a larger setting may balance out the dangers of a less customized ADL approach.
The secret is to be sincere about your loved one's priorities. If they mainly need companionship, light assistance, and take pleasure in busy environments, a large neighborhood can be a terrific fit. If they are modest, quickly overwhelmed, or require regular, hands-on aid with every ADL, a smaller setting normally serves them better.
The Role of Intimacy in Dementia and ADLs
Dementia makes complex every ADL. It affects memory, sequencing, spatial awareness, language, and emotional regulation. A lot of the most difficult habits households report - refusing showers, setting out during toileting, pacing all night - occur from anxiety and confusion, not stubbornness.
In a large, unfamiliar structure, somebody with dementia can feel lost several times a day. They may forget where the bathroom is, misinterpret complete strangers strolling down the hallway, or feel rushed by personnel who are trying to keep to a schedule. That anxiety shows up as resistance to care. Staff may describe the person as "difficult", when in truth the environment is merely too stimulating and impersonal.
An intimate assisted living or small memory care home shortens the distances and increases predictability. Homeowners see the very same caretakers, the very same kitchen, the same view out the window every early morning. Caretakers can use consistent scripts and routines: the same joke before showers, the exact same warm washcloth to start face washing. Gradually, this familiarity decreases resistance and makes it possible to preserve ADLs longer, even as cognitive decline progresses.
I remember a resident who had been declining showers in a bigger memory care unit for weeks. She clenched her fists, shouted, and attempted to hit staff. Household were told she "simply does not like baths anymore." When she moved into a 10-bed home, the caretaker observed that she unwinded whenever somebody hummed a particular hymn. They constructed a pre-shower ritual around that tune, redirected her to a portable shower she might see and control, and enabled her to hold a towel across her chest. Within 2 weeks, she was bathing routinely again. Absolutely nothing in her brain changed. The environment and the technique did.
For families navigating dementia, this is the heart of the small versus large question. Intimacy and repeating are not just "great to have" qualities. They are tools that straight support ADLs.
Practical Differences Families Will Notice
When you tour communities, a few of the most telling ideas are not in the pamphlet copy, but in the small interactions you witness. In a small home, you will often see caregivers and residents moving in and out of the kitchen area together, sharing small talk, and beginning ADLs naturally. A resident might be helped to wash up at the sink before breakfast, with a caregiver handing them a warm fabric and guiding each step.
In a large building, ADLs are more often set up and segmented. Showers might be "Monday, Wednesday, Friday at 10:30," and if your mother declined at 10:35, she might not get another attempt up until the next scheduled day. Meals are at set times, and late sleepers might get "space trays" if they miss the window, often without the same level of social engagement or help with eating.


Noise level, lighting, and room design matter for ADL success. Small homes tend to feel domestically familiar, which lowers anxiety for many seniors. Intense overhead lights and long hallways can be disorienting, especially for those with bad vision or cognitive decline. In a small setting, staff can more easily modify the environment. They might lower the lights throughout night care, play soft music during bathing times, or keep adaptive equipment within reach.
Families likewise discover how rapidly patterns are picked up. In small settings, if your father battles with buttons, somebody will most likely suggest pull-over shirts by the second or 3rd day, and you will see that shown in how they assist him dress. In a large setting, the very same observation may be buried amidst many residents' requirements, unless you or a strong advocate pushes it into the composed care strategy and follows up.
A Simple Comparison Checklist for ADL Support
When you tour or assess options, it helps to have a concentrated lens on ADLs, not just looks or activity calendars. Use this short checklist to compare how small and big settings might feel for your loved one:
- Ask staff to describe a typical morning for a resident who needs aid with bathing, dressing, and toileting. Listen for how much time they allow, and whether the routine sounds rushed or flexible. Observe how staff address homeowners in passing. Do they utilize names, touch, and eye contact, or are they primarily job focused and in a rush between rooms? Check how far rooms are from bathrooms and dining areas. Visualize your loved one making that trip three or four times a day. Ask how they adapt routines for someone who refuses or fears bathing. Search for specific, concrete examples, not unclear reassurances. Inquire about staff continuity. Do the same caretakers usually take care of the exact same citizens, or do projects alter frequently?
You are listening less for polished answers and more for consistency, detail, and indications that staff really understand their residents as individuals.
The Role of Respite Care in Screening Fit
One underused method for families is to deal with respite care as a trial run. Lots of assisted living neighborhoods, both large and small, deal brief stays varying from a couple of days to a few weeks. Throughout that time, your loved one resides in the community as a short-term resident, receiving the same senior care and elderly care services as long-term residents.
For ADLs, respite stays are extremely revealing. You will see how quickly staff discover your parent's regimens, how frequently call lights are addressed, whether clothing are put away appropriately, and if hygiene and grooming look preserved. Families in some cases discover that the excellent big neighborhood has a hard time to handle certain habits or ADL jobs, while a simple small home handles them efficiently. Other times, the reverse happens, particularly if your loved one is more social and independent than you realized.
Respite care also offers your parent a voice. Even a person with moderate cognitive decrease can typically inform you whether they feel taken care of, hurried, lonesome, or safe. Focus on whether they discuss "the people" by name in a small home, versus "the location" or "the structure" in a bigger one. That emotional connection usually associates highly with ADL success.
Balancing Dignity, Safety, and Independence
At the heart of all these choices is a balancing act: self-respect, security, and independence. Small, intimate assisted living settings tend to secure dignity and security by closely supporting ADLs and minimizing the opportunity of lapses. They also, when done well, support independence by offering locals just enough assist, not too much.
A great caretaker in a small home will understand that Mrs. Daniels can still brush her teeth individually if somebody simply sets out the tooth brush and cues her to start. In a busier environment, that same resident may have her teeth brushed for her since personnel are pushed for time. Over weeks and months, that difference speeds up decline.
Large neighborhoods, when genuinely well staffed and well led, can absolutely keep strong ADL support. Some accomplish this by creating small "communities" within a bigger campus, restricting each caregiver's location and encouraging relationship-based care. Others buy innovative training in dementia care techniques and work with adequate personnel to prevent persistent rushing. These designs sit closer to the "best of both worlds," but they tend to be at the higher end of the cost spectrum.
In completion, your choice will seldom be about perfection. It will have to do with trade-offs. Facilities versus intimacy. Variety versus predictability. On-site services versus day-to-day one-to-one time. For older grownups who require consistent, hands-on help with bathing, dressing, toileting, and mobility, smaller, more intimate settings typically tip the scales, due to the fact that they transform personnel hours into real, customized care.
Questions to Ask Yourself Before Deciding
As you weigh options, it assists to go back from marketing language and ask yourself a couple of grounded concerns about ADL assistance:
- Which environment will allow personnel to really understand my loved one's habits, fears, and choices around bathing, dressing, and toileting? If something fails - a fall, a rejection to shower, a bout of confusion - where are staff most likely to have time to problem-solve instead of default to crisis mode? Does my loved one gain more from everyday social variety or from predictable, familiar faces guiding them through vulnerable tasks? How much am I depending on amenities to make me feel much better versus what my loved one really uses and takes pleasure in? Could a brief respite care remain in one or two settings assist us see which environment better supports ADLs in practice?
Clear responses to these questions typically point strongly toward either a small or large setting as the much better first choice.
The decision about assisted living placement is one of the most individual in senior care. By focusing on how each environment truly manages ADLs, rather than only on looks or activity calendars, you provide your loved one the very best possibility at a life that feels safe, respectful, and as independent as possible.
BeeHive Homes of Albuquerque West provides assisted living care
BeeHive Homes of Albuquerque West provides memory care services
BeeHive Homes of Albuquerque West provides respite care services
BeeHive Homes of Albuquerque West offers support from professional caregivers
BeeHive Homes of Albuquerque West offers private bedrooms with private bathrooms
BeeHive Homes of Albuquerque West provides medication monitoring and documentation
BeeHive Homes of Albuquerque West serves dietitian-approved meals
BeeHive Homes of Albuquerque West provides housekeeping services
BeeHive Homes of Albuquerque West provides laundry services
BeeHive Homes of Albuquerque West offers community dining and social engagement activities
BeeHive Homes of Albuquerque West features life enrichment activities
BeeHive Homes of Albuquerque West supports personal care assistance during meals and daily routines
BeeHive Homes of Albuquerque West promotes frequent physical and mental exercise opportunities
BeeHive Homes of Albuquerque West provides a home-like residential environment
BeeHive Homes of Albuquerque West creates customized care plans as residents’ needs change
BeeHive Homes of Albuquerque West assesses individual resident care needs
BeeHive Homes of Albuquerque West accepts private pay and long-term care insurance
BeeHive Homes of Albuquerque West assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Albuquerque West encourages meaningful resident-to-staff relationships
BeeHive Homes of Albuquerque West delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Albuquerque West has a phone number of (505) 302-1919
BeeHive Homes of Albuquerque West has an address of 6000 Whiteman Dr NW, Albuquerque, NM 87120
BeeHive Homes of Albuquerque West has a website https://beehivehomes.com/locations/albuquerque-west/
BeeHive Homes of Albuquerque West has Google Maps listing https://maps.app.goo.gl/R1bEL8jYMtgheUH96
BeeHive Homes of Albuquerque West has Facebook page https://www.facebook.com/BeehiveABQW/
BeeHive Homes of Albuquerque West won Top Assisted Living Homes 2025
BeeHive Homes of Albuquerque West earned Best Customer Service Award 2024
BeeHive Homes of Albuquerque West placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Albuquerque West
What is BeeHive Homes of Albuquerque West monthly room rate?
Our base rate is $6,900 per month, but the rate each resident pays depends on the level of care that is needed. We do an initial evaluation for each potential resident to determine the level of care needed. The monthly rate is based on this evaluation. We also charge a one-time community fee of $2,000.
Can residents stay in BeeHive Homes of Albuquerque West until the end of their life?
Usually yes. There are exceptions, such as when there are safety issues with the resident, or they need 24 hour skilled nursing services.
Does Medicare or Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living as a covered benefit. Some assisted living facilities are Medicaid providers but we are not. We do accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program.
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock.
Do we allow pets at Bee Hive?
Yes, we allow small pets as long as the resident is able to care for them. State regulations require that we have evidence of current immunizations for any required shots.
Do we have a pharmacy that fills prescriptions?
We do have a relationship with an excellent pharmacy that is able to deliver to us and packages most medications in punch-cards, which improves storage and safety. We can work with any pharmacy you choose but do highly recommend our institutional pharmacy partner.
Do we offer medication administration?
Our caregivers are trained in assisting with medication administration. They assist the residents in getting the right medications at the right times, and we store all medications securely. In some situations we can assist a diabetic resident to self-administer insulin injections. We also have the services of a pharmacist for regular medication reviews to ensure our residents are getting the most appropriate medications for their needs.
Where is BeeHive Homes of Albuquerque West located?
BeeHive Homes of Albuquerque West is conveniently located at 6000 Whiteman Dr NW, Albuquerque, NM 87120. You can easily find directions on Google Maps or call at (505) 302-1919 Monday through Sunday 10am to 7pm
How can I contact BeeHive Homes of Albuquerque West?
You can contact BeeHive Homes of Albuquerque West by phone at: (505) 302-1919, visit their website at https://beehivehomes.com/locations/albuquerque-west, or connect on social media via Facebook
The Indian Pueblo Cultural Center offers engaging exhibits and cultural education ideal for assisted living and memory care residents during senior care or respite care outings.